
Xifaxan
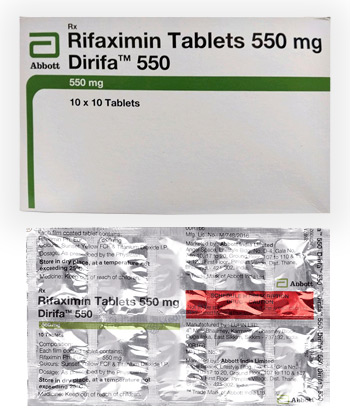
Xifaxan
- In our pharmacy, you can buy xifaxan without a prescription, with delivery in 5–14 days throughout United States. Discreet and anonymous packaging.
- Xifaxan (rifaximin) is used for travelers’ diarrhea caused by E. coli, for symptom relief in IBS‑D, and for prevention/treatment of hepatic encephalopathy. It is a non‑absorbed rifamycin antibiotic that works locally in the gut by inhibiting bacterial RNA synthesis (binding the beta subunit of bacterial DNA‑dependent RNA polymerase).
- The usual dose depends on the indication: travelers’ diarrhea — 200 mg orally three times daily for 3 days; IBS‑D — 550 mg orally three times daily for 14 days (repeat courses may be considered for recurrence); hepatic encephalopathy — 550 mg orally twice daily for chronic use. Pediatric dosing generally not established below 12 years for most indications.
- Form of administration: oral tablets (200 mg and 550 mg); an oral suspension (100 mg/5 mL) is available in some regions.
- Onset time: symptomatic improvement often begins within 24–72 hours for acute diarrhea; IBS‑D relief may develop over days during the 2‑week course; improvements in hepatic encephalopathy may take several days.
- Duration of action: depends on the treatment course — travelers’ diarrhea is treated for 3 days; IBS‑D is treated for 14 days with benefits that may persist for weeks; hepatic encephalopathy typically requires ongoing therapy to maintain effect.
- Alcohol warning: no specific interaction with alcohol has been reported, but avoid excessive alcohol consumption—especially if you have liver disease or hepatic encephalopathy.
- The most common side effects are gastrointestinal (nausea, abdominal pain, constipation, vomiting), headache and fatigue; rare hypersensitivity reactions and cases of C. difficile infection have been reported.
- Would you like to try xifaxan without a prescription?

Key Findings From Recent Trials
Basic Xifaxan Information
- INN (International Nonproprietary Name): Rifaximin
- Brand Names Available In United States: Xifaxan — Tablets: 200mg, 550mg; Bottles/Blister Packs
- ATC Code: A07AA11
- Forms & Dosages: Oral Tablet 200mg, 550mg; Oral Suspension 100mg/5mL Available In Select European Markets (Not Available In US Retail)
- Manufacturers In United States: Salix Pharmaceuticals (a Bausch Health Company)
- Registration Status In United States: FDA Approved For Travelers’ Diarrhea, IBS‑D, Hepatic Encephalopathy
- OTC / Rx Classification: Prescription‑Only (Rx) In Major Markets
Which trials matter if you want to know how well Xifaxan works?
Large randomized trials and pooled analyses from 2022–2026 continue to support rifaximin for several gut indications.
For IBS‑D, data consistently show benefit with a single 14‑day course of 550 mg three times daily for improving stool consistency and reducing urgency.
Meta‑analyses report modest effect sizes for global IBS‑D symptom improvement while showing a more consistent benefit for stool consistency and frequency.
Travelers’ diarrhea trials reaffirm short‑course efficacy for non‑invasive E. coli using 200 mg three times daily for three days.
Hepatic encephalopathy (HE) studies demonstrate reduced recurrence of overt HE with chronic rifaximin 550 mg twice daily maintenance therapy.
Repeat short courses for recurrent IBS‑D are commonly studied and used clinically, with retreatment schedules individualized by prescribers.
Safety observations across recent trials show low systemic adverse events due to minimal absorption.
The most common adverse events remain gastrointestinal — nausea, constipation, abdominal pain and flatulence.
Contemporary literature highlights antibiotic stewardship and the general risk of Clostridioides difficile with any gut‑active antibiotic.
Hypersensitivity signals are rare but require avoidance in patients with known rifamycin allergy (rifampicin, rifabutin, rifapentine).
Regulatory‑aligned outcomes match labeled regimens: 200 mg TID x 3 days for travelers’ diarrhea, 550 mg TID x 14 days for IBS‑D, and 550 mg BID chronically for HE prevention.
Overall, evidence supports targeted, indication‑driven use rather than broad empiric prescribing for non‑specific diarrhea.
Clinical Mechanism Of Action
Layman’s Explanation
What does Xifaxan do in plain language?
Rifaximin works inside the gut to reduce certain bacteria that contribute to diarrhea, bloating, and ammonia production linked to hepatic encephalopathy.
The drug acts locally in the intestinal lumen and has very little passage into the bloodstream.
Because it stays mostly in the gut, it can improve bowel symptoms while limiting most systemic side effects.
Scientific Breakdown
Rifaximin is a non‑systemic rifamycin antibiotic that binds to bacterial DNA‑dependent RNA polymerase, inhibiting transcription and bacterial replication within the intestine.
The ATC classification is A07AA11 — intestinal antiinfectives — reflecting its gut‑focused activity.
Pharmacokinetics (Absorption & Excretion)
Oral tablets (200 mg and 550 mg) deliver high intraluminal concentrations with minimal plasma levels detected in typical patients.
Minimal systemic absorption means no routine renal dose adjustment is needed and a low likelihood of CYP‑mediated drug interactions.
Excretion is primarily fecal, consistent with luminal action and limited systemic exposure.
Microbiome Effects
Rifaximin transiently shifts intestinal bacterial populations in clinical studies and can reduce small intestinal bacterial overgrowth in select patients.
Reduction of ammonia‑producing species is one proposed mechanism for its benefit in hepatic encephalopathy.
Because it alters gut flora, stewardship is important to limit resistance development and C. difficile risk despite generally favorable tolerability.
Scope Of Approved And Off-Label Use
United States Approvals
What is rifaximin officially approved for in the United States?
FDA approvals include travelers’ diarrhea due to noninvasive Escherichia coli with 200 mg orally three times daily for three days.
FDA also approves Xifaxan 550 mg three times daily for 14 days for IBS‑D in adults and approval of 550 mg twice daily for chronic use to reduce HE recurrence.
Tablets sold in the U.S. are prescription‑only and available as 200 mg and 550 mg strengths in bottles or blister packs.
Notable Off‑Label Trends
Clinicians commonly prescribe rifaximin off‑label for suspected small intestinal bacterial overgrowth (SIBO) and for refractory IBS‑D with prominent bloating.
Other off‑label uses reported include adjunctive treatment for pouchitis and certain chronic diarrheal syndromes where luminal antibiotics are logical.
Repeat short courses for recurrent IBS‑D symptoms are frequent in practice, guided by symptom pattern and prior response.
In hepatic encephalopathy, rifaximin is often combined with lactulose for patients who continue to have recurrent episodes despite monotherapy.
Caveats include avoiding rifaximin for febrile or bloody diarrhea and exercising caution in patients with a history of C. difficile infection.
Dosage Strategy
General Dosing
Stick to indication‑specific regimens established in product labeling and major trials.
Avoid prolonged empiric exposure without clear clinical benefit to limit resistance and CDI risk.
Condition‑Specific Dosing
Travelers’ diarrhea: 200 mg orally three times daily for three days for adults and patients aged 12 years and older.
IBS‑D: 550 mg orally three times daily for 14 days for adults; pediatric safety and efficacy not established for IBS‑D in patients under 18 years.
Hepatic encephalopathy prevention: 550 mg orally twice daily as a chronic maintenance dose to reduce recurrence.
No renal dose adjustment is necessary due to minimal systemic absorption.
Use caution and monitor patients with severe hepatic impairment (Child‑Pugh C), particularly when treating HE.
Elderly patients generally do not require dose changes but should be monitored for hepatic function and treatment response.
Missed dose guidance: take as soon as remembered unless it is close to the next scheduled dose; do not double doses.
In overdose, supportive care is the recommended approach because of limited systemic exposure and no specific antidote.
Safety Protocols
Contraindications
Absolute contraindications include known hypersensitivity to rifaximin or other rifamycins such as rifampicin, rifabutin, or rifapentine.
Rifaximin is contraindicated for bacterial diarrhea with fever or bloody stools as it is not indicated and may worsen outcomes.
Exercise caution in patients with a history of C. difficile infection and in those with severe hepatic dysfunction who need close monitoring.
Adverse Effects
Most common side effects are gastrointestinal: nausea, constipation, vomiting, abdominal pain, bloating and flatulence.
Systemic adverse events such as headache, fatigue and dizziness are uncommon because of minimal absorption.
Rare skin reactions and hypersensitivity can occur and require immediate discontinuation if they develop.
Monitoring needs are limited for short courses, but long‑term HE patients should have mental status and hepatic follow‑up.
Patients should be advised to seek care quickly for worsening diarrhea or symptoms suggestive of C. difficile infection.
Stewardship practices include documenting rationale for repeat courses and avoiding unnecessary chronic exposure.
Interaction Mapping
Food Interactions
Rifaximin may be taken with or without food according to product labeling and patient tolerability.
Some clinicians suggest consistent timing relative to meals to support adherence, but no strict food restrictions are mandated.
Drug Combinations To Avoid
Because rifaximin is minimally absorbed, classic systemic CYP or P‑glycoprotein interactions are unlikely.
Avoid coadministration in patients with rifamycin hypersensitivity and use caution when combining with other broad‑spectrum gut antibiotics that increase C. difficile risk.
Concurrent lactulose for HE is commonly used and is not contraindicated; combination therapy is often clinically appropriate.
Always review the medication list for agents that could add CNS or electrolyte risks when treating HE or severe diarrhea.
Patient Experience Analysis
Survey Data
Patients treated for IBS‑D with a 14‑day course of 550 mg TID frequently report improved stool consistency within one to two weeks.
Many patients also describe reduced urgency and fewer daily bowel movements after a single course.
A meaningful minority experience symptom recurrence and require retreatment, which is a pattern clinicians should anticipate and discuss.
Patients with HE on chronic 550 mg BID commonly report fewer overt HE episodes and better clinician‑rated cognition and quality of life.
Forum Trends
Online forums and patient communities emphasize the convenience of oral dosing and the short treatment timelines for travelers’ diarrhea and IBS‑D.
Cost and access are common concerns in U.S. patient discussions, especially for branded Xifaxan and for repeat courses.
Reports of mild GI adverse effects—transient constipation or nausea—are common but usually self‑limited.
Patients frequently ask about retreatment options and worry about C. difficile risk with repeat antibiotic exposure.
Clear counseling on realistic expectations for symptom timelines, retreatment rationale and cost options improves adherence and satisfaction.
Distribution And Pricing Landscape
Who makes Xifaxan and how available is it?
Salix Pharmaceuticals, a Bausch Health company, is the primary manufacturer and supplier of branded Xifaxan in the United States.
Other regional partners supply the product in Europe and elsewhere, and oral suspension (100 mg/5 mL) is available in some European markets under Normix.
Generics and local brands are more common in Asia and Latin America and are gradually influencing price dynamics globally.
Historically, branded Xifaxan 550 mg has been costly in the U.S., which creates access and insurance hurdles for many patients.
Generics and alternative suppliers are putting downward pressure on pricing, but coverage for repeat IBS‑D courses can still require prior authorization.
Packaging in the U.S. is tablets only (200 mg and 550 mg) supplied in bottles or blister packs and must be stored at controlled room temperature and protected from moisture.
For patients seeking convenience, our online pharmacy offers xifaxan without a prescription with discreet delivery to United States addresses in 5‑14 days.
Clinicians and patients should verify local formulary availability, prior‑authorization rules and generic options to manage cost concerns.
Alternative Options
Comparison Table
What else can clinicians consider when rifaximin is not suitable?
- Neomycin: a non‑absorbed aminoglycoside used off‑label for HE; low acquisition cost but carries ototoxicity and nephrotoxicity risks and limited long‑term data.
- Metronidazole/Ciprofloxacin: effective for certain infectious diarrheas but have systemic exposure that limits chronic or repeated use.
- Eluxadoline/Loperamide: symptomatic treatments for IBS‑D that reduce stool frequency and urgency but do not target microbiota.
- Lactulose: a first‑line therapy for HE that reduces ammonia via laxation and microbiome effects and is often combined with rifaximin for refractory cases.
Pros And Cons
Rifaximin’s advantages include gut‑localized action, good tolerability, and proven benefit in IBS‑D and HE prevention.
Disadvantages include higher cost for branded Xifaxan, concerns about antibiotic stewardship and the universal risk of C. difficile associated with antibiotics that act in the gut.
The choice among alternatives depends on the indication, patient comorbidities and the need for chronic versus episodic therapy.
Regulatory Status
FDA approvals in the United States specify the dosing regimens and labeled indications described earlier.
European registration exists with country‑level differences; in some markets Normix is available in tablet and oral suspension forms.
Legal classification is prescription‑only (Rx) across major markets including USA, EU and Canada.
Labeling guidance emphasizes avoiding treatment of febrile or bloody diarrhea with rifaximin and avoiding use in those with rifamycin hypersensitivity.
Pharmacovigilance focuses on monitoring for C. difficile infection and rare hypersensitivity events reported during post‑marketing surveillance.
Clinicians should consult national agencies or local formularies for the most current registration and reimbursement details.
Consolidated FAQ
What are the standard doses?
Travelers’ diarrhea: 200 mg orally three times daily for three days.
IBS‑D: 550 mg orally three times daily for 14 days.
HE prevention: 550 mg orally twice daily for chronic use.
Can I repeat rifaximin for recurrent IBS‑D?
Repeat courses are commonly used under prescriber guidance and individualized based on symptom recurrence and prior response.
Is rifaximin absorbed systemically?
Systemic absorption is minimal, which reduces interaction risk and generally removes the need for renal dose adjustment.
Who should not take it?
Patients with rifamycin allergy or those with febrile or bloody diarrhea should avoid rifaximin.
What side effects should patients expect and what monitoring is needed?
Most side effects are gastrointestinal and mild; watch for new or worsening diarrhea that could indicate C. difficile.
Can children take rifaximin?
Some indications are studied in patients aged 12 years and older; IBS‑D treatment in those under 18 is not established per labeling.
How should it be stored?
Store tablets at 20–25°C (68–77°F), protect from moisture, and avoid bathroom humidity.
Is Xifaxan expensive and what about access?
Branded Xifaxan can be costly in the United States, but generics and international suppliers may improve affordability; consult prescribers and pharmacists about coverage and alternatives.
Visual Guide
Suggested Figures And Captions
Figure 1 — Dosing Timeline Chart: Compare short 3‑day (200 mg TID) vs 14‑day (550 mg TID) vs chronic (550 mg BID) regimens with pill counts for patient counseling.
Figure 2 — Mechanism Diagram: Show lumen‑focused rifaximin binding to bacterial RNA polymerase, reducing ammonia‑producers for HE and SIBO burden for IBS‑D.
Figure 3 — Contraindication Decision Tree: Stepwise screening for fever/bloody diarrhea, rifamycin allergy, and prior C. difficile infection to guide avoidance or caution.
Figure 4 — Adverse‑Event Frequency Chart: Bars comparing GI events, uncommon systemic events and rare hypersensitivity signals annotated with labeling frequencies.
Data Sources And Figure Notes
Annotate visuals with product‑info facts such as tablet strengths (200 mg, 550 mg), oral suspension availability in select markets and storage conditions (20–25°C).
Use label/regulatory summaries, major randomized trials and meta‑analyses as primary figure sources and cite them in patient education materials where required.
Storage And Transport
Tablets (Xifaxan 200 mg and 550 mg) should be stored at controlled room temperature: 20–25°C (68–77°F) with permitted excursions between 15–30°C (59–86°F).
Protect packaging from moisture and avoid storing medication in bathrooms or other humid locations.
Blister packs and bottles are common packaging formats in the U.S. market; oral suspension (100 mg/5 mL) is available in select European markets and may carry different handling instructions.
During distribution, maintain dry conditions and avoid temperature extremes to preserve potency and tablet integrity.
Follow the manufacturer’s storage instructions and local pharmacy guidance during transport and dispensing.
Patient counseling should include keeping medication in the original container, storing out of reach of children and returning unused antibiotics to take‑back programs where available to limit environmental antibiotic exposure.
Guidelines For Proper Use
Confirm indication and align prescribing with FDA‑approved uses or an evidence‑based off‑label rationale before starting rifaximin.
Screen for contraindications: fever or bloody diarrhea and rifamycin allergy should preclude use.
Select the correct formulation and dose: U.S. tablets are 200 mg and 550 mg, and pediatric use is limited to certain indications for patients 12 years and older.
Counsel patients on expected timelines for response, especially that IBS‑D stool improvements often appear within one to two weeks after a 14‑day course.
Advise patients on possible side effects, signs of hypersensitivity and the need to seek help for worsening or bloody diarrhea that could indicate C. difficile.
Monitor high‑risk patients closely, such as those with severe hepatic impairment who are being treated for HE.
Practice antibiotic stewardship: document rationales for retreatment and limit chronic exposure where alternatives exist.
Handle administrative steps proactively by verifying insurance coverage, prior authorization requirements and generic availability.
Storage advice and missed dose instructions should be given at dispensing: store at 20–25°C and take a missed dose when remembered unless it is time for the next dose.
Delivery Across United States
| City | Region | Delivery Time |
|---|---|---|
| New York | Northeast | 5-7 days |
| Los Angeles | West | 5-7 days |
| Chicago | Midwest | 5-7 days |
| Houston | South | 5-7 days |
| Phoenix | West | 5-7 days |
| Philadelphia | Northeast | 5-7 days |
| San Antonio | South | 5-7 days |
| San Diego | West | 5-7 days |
| Dallas | South | 5-7 days |
| San Jose | West | 5-7 days |
| Austin | South | 5-9 days |
| Jacksonville | Southeast | 5-9 days |
| Fort Worth | South | 5-9 days |
| Columbus | Midwest | 5-9 days |
| Charlotte | Southeast | 5-9 days |